

The popular suggestion to take magnesium for sleep apnea skips an important question: does feeling more relaxed mean breathing stays uninterrupted during sleep? Those aren't the same outcome. Research on magnesium and sleep apnea offers some interesting associations, but it doesn't establish a magnesium pill as a treatment for a collapsing airway.
For adults interested in healthy aging, that distinction leaves room for curiosity without turning a supplement into a promise. Magnesium status, sleep symptoms, food choices, and supplement safety are related topics, but each answers a different question.
Table of Contents
- Why Magnesium and Sleep Apnea Get Mentioned Together
- How Magnesium Works in the Body During Sleep
- What the Research Actually Shows
- Why Older Adults Are an Important Audience
- Food First, Supplements Second
- Safe Dosing, Kidney Health, and Medication Interactions
- A Friendly Checklist for Patients and Caregivers
- Bringing It All Together
Why Magnesium and Sleep Apnea Get Mentioned Together
The VA/DoD clinical-practice summary on insomnia and obstructive sleep apnea provides a useful starting point: evidence was insufficient to recommend magnesium either for or against insomnia treatment. That uncertainty matters before making the larger leap from a possible sleep aid to an apnea treatment.
Insomnia concerns difficulty falling asleep or staying asleep. Obstructive sleep apnea, often shortened to OSA, concerns breathing interruptions associated with airway obstruction during sleep. Someone can talk about a bad night's sleep without distinguishing these experiences, but researchers need to distinguish them.
That helps explain why the magnesium conversation gets confusing. Consumer discussions often put relaxation, falling asleep, waking refreshed, and breathing normally into the same basket. A supplement claim about one of those experiences doesn't automatically apply to the others.
Different meanings of better sleep
Consider a hypothetical example: someone takes magnesium and feels that bedtime is less restless. That's a report about their experience, not a measurement of whether their airway remained open.
Researchers separate several outcomes:
- Sleep latency means the time it takes to fall asleep.
- Total sleep time describes how much sleep someone gets.
- Breathing measurements describe interruptions and oxygen changes during sleep.
- Daytime function concerns how someone feels and manages activities while awake.
These outcomes can answer different questions, even when they all appear under the heading of sleep health.
A useful distinction: Feeling that sleep improved doesn't establish that apnea improved.
Magnesium gets mentioned alongside OSA because researchers have observed relationships between magnesium status and the condition. Biological questions about muscles, nerves, and inflammation add reasons to investigate that relationship, but they aren't proof that supplementation changes airway obstruction.
For older adults and caregivers, the most relevant distinction isn't between natural and unnatural products. It's between a nutritional question, a sleep-symptom question, and an airway-treatment question. Keeping them separate makes research easier to understand and conversations with healthcare professionals more specific.
How Magnesium Works in the Body During Sleep
The retrospective study of magnesium, inflammation, and OSA helps explain why researchers became interested in this connection. In 68 people newly diagnosed with OSA and 30 matched comparison participants, researchers found lower magnesium and higher C-reactive protein in the OSA group; magnesium and CRP were inversely correlated (p<0.0001), and magnesium also had negative correlations with the apnea-hypopnea index and oxygen desaturation index.
The everyday biological picture is that magnesium participates in body processes rather than acting as a nighttime switch. Discussions about its involvement in enzyme activity, muscle function, and nerve signaling help explain the research interest. However, those roles don't establish that taking extra magnesium produces deeper sleep or keeps the upper airway open.
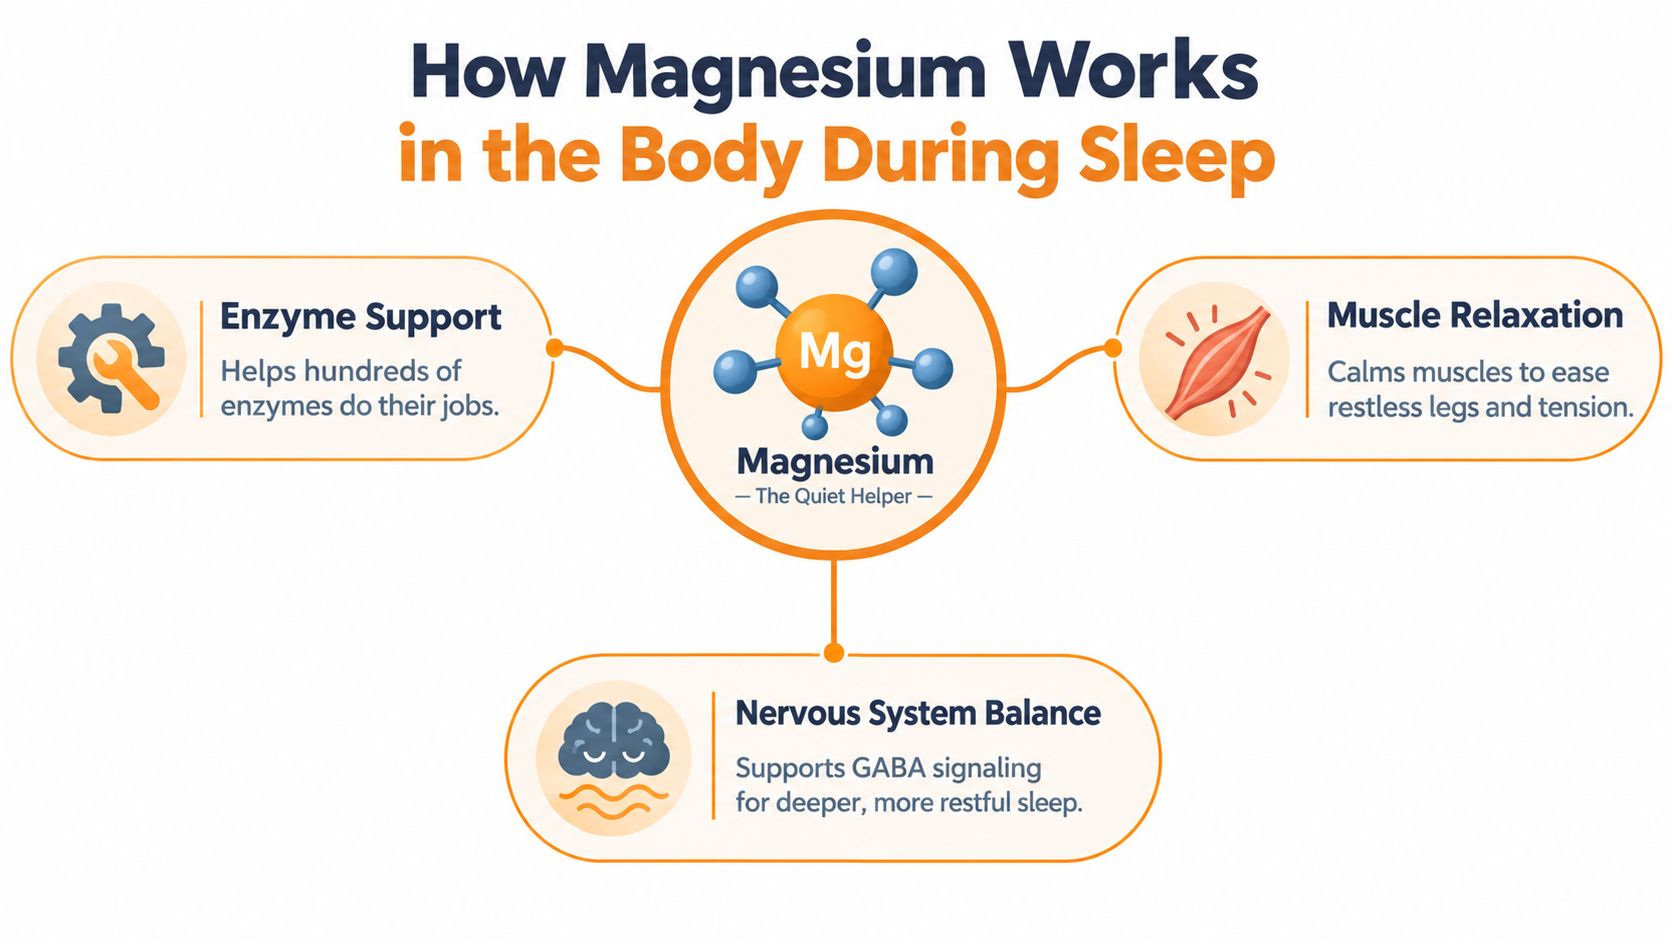
A helper isn't a treatment mechanism
Think of magnesium's place in the body like a component in a larger system. Knowing that a component matters doesn't tell us whether adding more changes the system's performance. Researchers still need to examine what happens when people receive a supplement, rather than infer the answer from basic biology.
The same caution applies to muscle relaxation. The phrase sounds reassuring, but relaxation and airway stability aren't interchangeable concepts. A general statement about muscle function can't establish an effect on sleep-related breathing.
Inflammation adds another layer. C-reactive protein, or CRP, is an inflammation marker. In the study described above, lower magnesium tended to occur alongside higher CRP, more frequent breathing interruptions, and more frequent oxygen drops.
The relationship could run in different directions
Those findings don't identify which change came first. Researchers can investigate whether magnesium status contributes to physiological stress, whether disrupted sleep influences magnesium status, or whether other factors help explain both.
- A plausible mechanism offers an explanation worth testing.
- An observed correlation shows that measurements vary together.
- A demonstrated treatment effect requires evidence that an intervention changes the relevant outcome.
For a broader vocabulary around sleep quality, the explanation of what restorative sleep means offers a separate educational starting point. Restorative sleep is a broader topic than whether a particular nutrient changes apnea measurements.
What the Research Actually Shows
The systematic review and meta-analysis of serum magnesium in OSA gathered evidence covering 312 people with OSA; across three studies, serum magnesium was lower than in comparison groups, with a pooled effect size of -1.22 and a 95% confidence interval from -2.24 to -0.21. Those figures describe a difference between groups, not a response to magnesium treatment.
Serum magnesium means magnesium measured in the blood. An effect size summarizes the difference researchers observed across studies, while a confidence interval expresses statistical uncertainty around that estimate. The negative direction here indicates lower levels in the OSA groups.
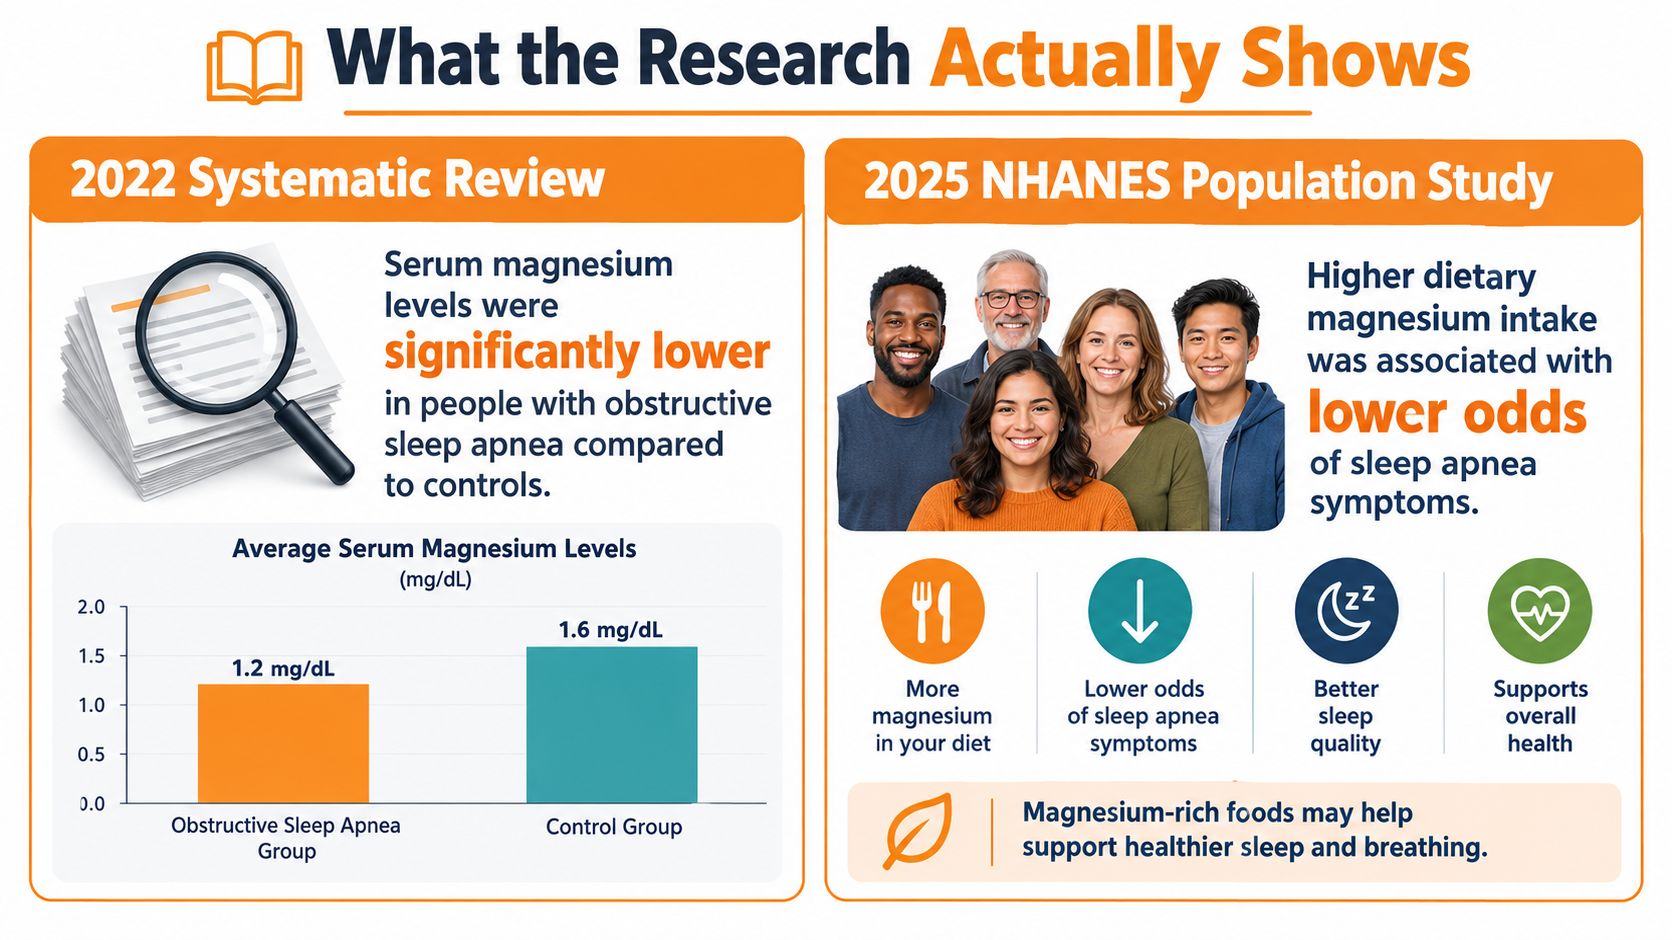
The image's intake-and-symptom wording needs caution. Blood concentration, a deficiency score, and supplement use aren't equivalent measurements, and an association isn't evidence of symptom reduction after treatment.
What the severity finding means
In one analysis included in that review, serum magnesium of at least 1.98 mg/dL was associated with lower odds of severe OSA, with an odds ratio of 0.54, a 95% confidence interval of 0.38 to 0.88, and p=0.006. These are findings from the same review linked at the section opening.
An odds ratio compares odds between groups. It isn't a guaranteed outcome for a person, and this threshold isn't a supplement target. The analysis didn't establish that raising someone's magnesium above it would change their apnea.
The review also complicates the idea that everyone with OSA has a deficiency. Among 251 OSA patients, pooled mean magnesium was 1.90 mg/dL, with a 95% confidence interval of 1.77 to 2.04, overlapping the reported normal range of 1.82 to 2.30 mg/dL, again as reported in the opening-linked review.
A group average can overlap a laboratory reference range while researchers still observe an association with disease severity.
Different studies ask different questions
The population analysis discussed below used a magnesium deficiency score rather than just a blood measurement. Separate concentration and supplement-use studies also produced different findings.
| Research measurement | What it can describe | What it doesn't establish |
|---|---|---|
| Blood magnesium | An association with OSA presence or severity | Whether taking magnesium treats OSA |
| A deficiency score | A relationship within a population dataset | A diagnosis for an individual |
| Reported supplement use | An association involving people who report use | A controlled treatment response |
The inflammation findings described earlier fit this observational picture. Taken together, the research is a reason to keep investigating magnesium status, not a basis for treating a blood-level association as a supplement benefit.
Why Older Adults Are an Important Audience
The population analysis using a magnesium deficiency score examined adults aged 20 and older using survey data from 2005 through 2014. Participants scoring above 1 had 64% higher odds of OSA before additional adjustments, corresponding to OR 1.64 and a 95% confidence interval of 1.32 to 2.05; adjusted models reported smaller associations, with ORs of 1.36 and 1.30.
This wasn't an older-adult-only study. Its findings therefore shouldn't be presented as a precise estimate for older people, or as evidence that age alone determines magnesium needs.
The changes after adjustment are useful for understanding observational research. Researchers account for measured variables to examine whether an association persists, but that process doesn't turn a cross-sectional dataset into a treatment experiment.

An everyday question can involve several details
An older adult might ask about magnesium after hearing a friend describe it as a sleep aid. A family member might be more interested in snoring, while the person themselves wants to understand an unfamiliar blood-test result. These are hypothetical situations, not reported case studies.
The questions differ:
- Food patterns concern what someone regularly eats and whether their nutritional needs are being met.
- Sleep observations concern what the person experiences and what someone else notices.
- Product use concerns supplements, prescriptions, and over-the-counter medicines.
- Kidney function concerns how the body handles substances, including supplemental magnesium.
None of those details can be inferred from someone's age or whether they have OSA.
Shared decisions without taking over
The safety literature discussed later identifies reduced renal clearance and multiple medicines as relevant considerations for older adults. That makes a blanket statement such as magnesium is harmless a poor summary of the evidence.
Shared decision-making means that the person's goals, preferences, and circumstances remain part of the conversation. A caregiver's observations can add context without replacing the older adult's own account.
For someone focused on independence, the research question is therefore more useful when phrased specifically: what does magnesium status mean in this person's broader situation? That's different from assuming that every older adult with poor sleep needs the same product.
Food First, Supplements Second
The research reporting differing magnesium concentration and supplement-use findings illustrates why food, blood levels, and pills shouldn't be treated as interchangeable evidence. Compared with the lowest magnesium quartile, the second had OR 0.31, with a 95% confidence interval of 0.09 to 0.96, and the third had OR 0.26, with a 95% confidence interval of 0.07 to 0.82; a later observational analysis reported no association between magnesium supplement use and sleep-apnea risk.
A quartile is a group formed by dividing a dataset into ordered portions. These comparisons concern measured magnesium concentration, not proof that selecting a particular food or supplement changes sleep-related breathing.
The null supplement finding matters just as much as the concentration associations. Researchers also noted uncertainty about mechanisms and the possible influence of other trace elements and clinical variables.
Common Magnesium Sources at a Glance
The following table identifies familiar food categories and supplement names. It isn't an absorption ranking, a shopping recommendation, or an apnea-treatment comparison.
| Source | Typical Form | Why People Choose It |
|---|---|---|
| Leafy greens | Spinach and other greens in meals | A food-based approach to magnesium |
| Nuts and seeds | Snacks or meal ingredients | A way to include magnesium-containing foods |
| Beans and whole grains | Ingredients in everyday meals | A food choice rather than a separate supplement |
| Certain fish | Part of a mixed diet | Another food category in the nutrition conversation |
| Magnesium citrate | A named supplement form | A product considered separately from food intake |
| Magnesium glycinate | A named supplement form | Another option discussed in supplement reviews |
| Magnesium oxide | A named supplement form | A different formulation requiring its own context |
“Food first” is a way to organize the discussion, not evidence that a magnesium-rich meal treats apnea. Food choices concern a person's overall eating pattern; a supplement introduces a separate question about amount, formulation, tolerance, and purpose.
No established best form for apnea
The research summarized here doesn't establish citrate, glycinate, or oxide as the best magnesium form for OSA. It also doesn't provide a basis for promising better breathing from claims about absorption or gentleness.
The broader relationship between nutrition and chronic conditions is a separate educational topic. For magnesium and sleep apnea, the important boundary remains clear: nutritional adequacy and apnea control are different outcomes.
Safe Dosing, Kidney Health, and Medication Interactions
The review summarizing NCCIH magnesium safety guidance reports an adult tolerable upper intake level of 350 mg per day from supplements and medications unless a clinician recommends otherwise. It identifies diarrhea, nausea, and abdominal cramping as common effects of excess intake and highlights clinician review for older adults with reduced renal clearance.
That number isn't a suggested sleep dose. It also isn't a target that every adult needs to reach. The distinction between an upper intake limit and an intended amount matters when a product label is read as a wellness instruction.
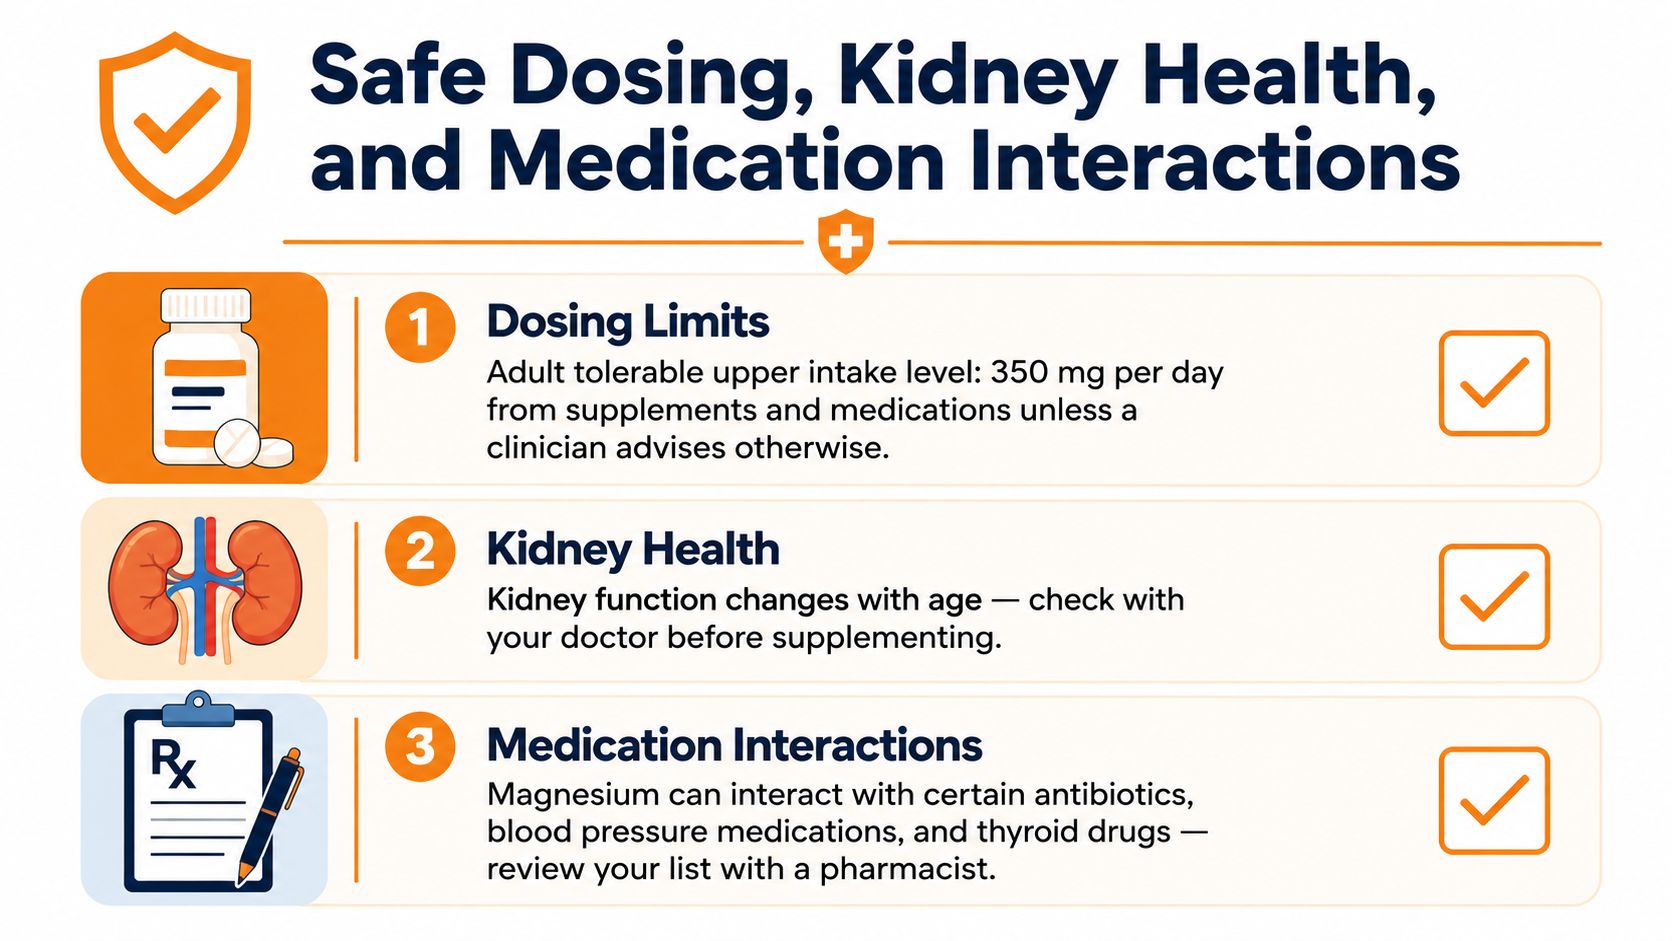
Kidney health changes the context
Renal clearance describes removal through the kidneys. When that clearance is reduced, the safety question differs from the question of whether a supplement might affect sleep symptoms.
The review's relevance to older adults isn't that every older person has impaired kidney function. It's that kidney status is part of the context needed to interpret supplemental intake.
Safety perspective: An over-the-counter label doesn't establish that a product is suitable for every person.
Medication use adds another layer. A discussion can include prescription medicines, over-the-counter products, and supplements rather than considering each bottle in isolation.
Questions for a medication review
Examples of medicine categories relevant to that conversation include certain antibiotics, bisphosphonates, diuretics, and proton pump inhibitors. A category name alone doesn't establish an interaction for every product within it, and the evidence summarized here doesn't support a universal spacing schedule.
Useful review questions include:
- Total product exposure, Does magnesium appear in more than one supplement or medication?
- Exact medicine names, What prescriptions and over-the-counter products are being used?
- Purpose, Is magnesium being considered for nutritional adequacy, a documented deficiency, or a sleep claim?
- Tolerance and kidney context, What information would a clinician need to assess suitability?
The explanation of medication timing offers broader context for timing questions. It isn't a substitute for an individualized interaction review.
A safety discussion doesn't need to become a do-it-yourself dosing plan. Its purpose is to clarify which details a clinician or pharmacist would need, especially when several products and health considerations overlap.
A Friendly Checklist for Patients and Caregivers
The insomnia-and-OSA summary and magnesium safety review cited earlier support a question-focused checklist rather than a supplement experiment. The aim is to distinguish everyday wellness routines from symptoms and product questions that require professional interpretation.
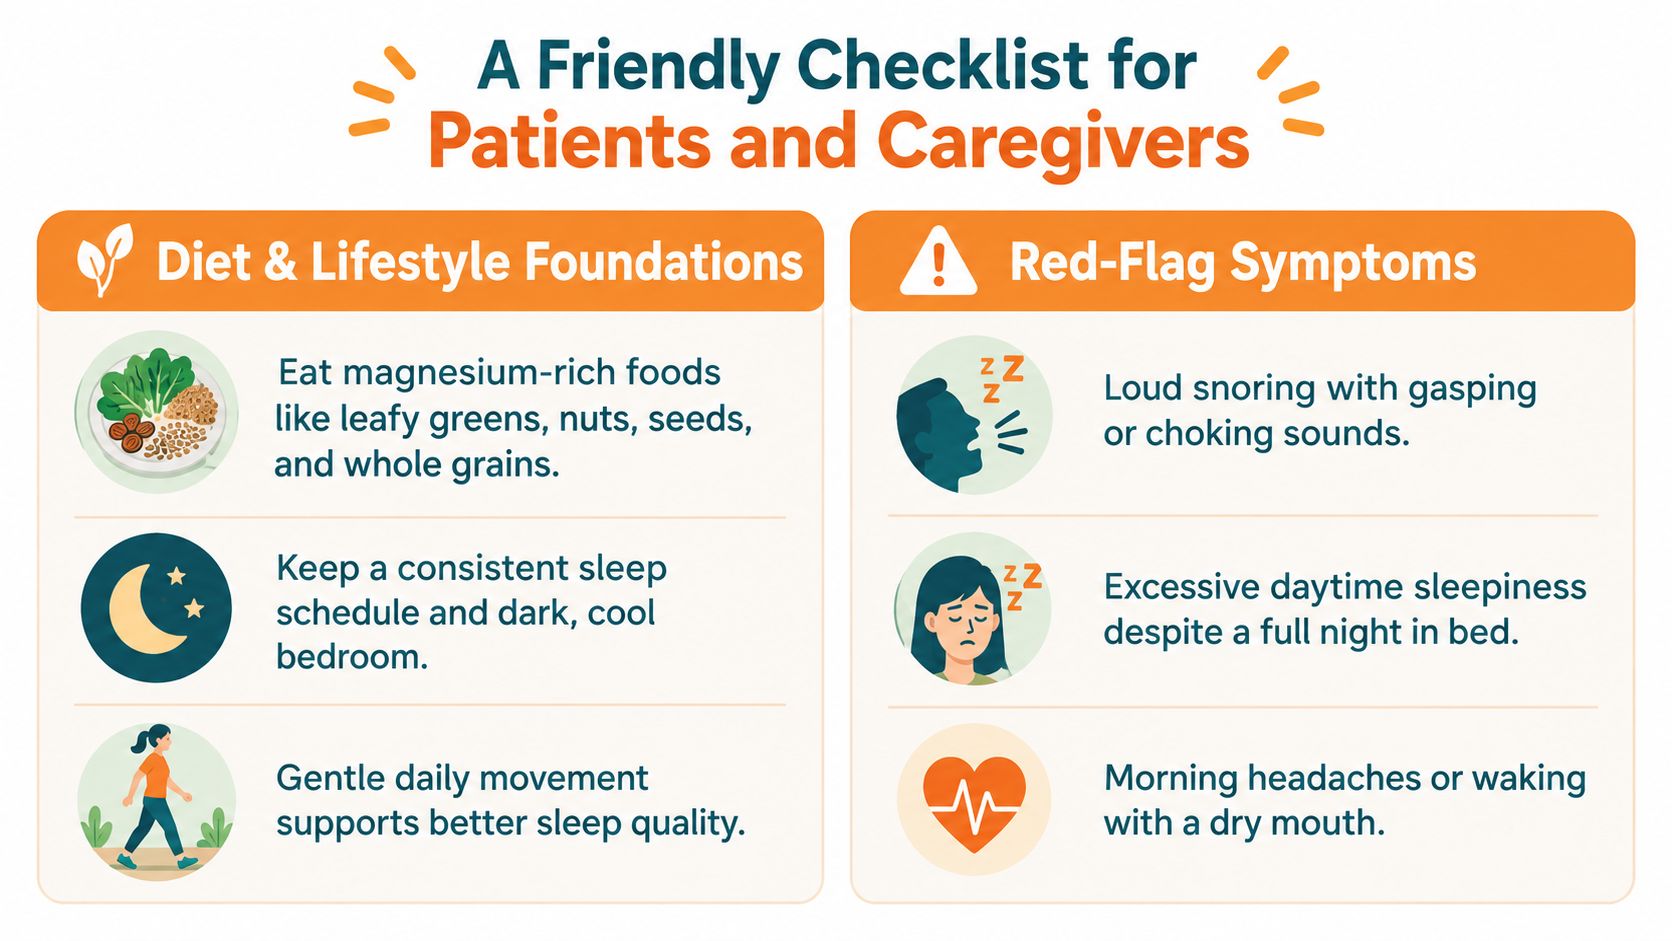
Conversation prompts
- Everyday routines, What do meals, movement, bedtime, and the sleeping environment currently look like? These describe context, not an apnea treatment.
- Sleep experiences, Is the main concern falling asleep, staying asleep, or functioning during the day?
- Observed breathing, Has someone noticed persistent snoring, breathing pauses, or gasping? Such observations don't establish a diagnosis, but they belong in an OSA evaluation conversation.
- Other symptoms, Morning headaches and daytime sleepiness are also relevant to that discussion rather than evidence that magnesium is missing.
- Product questions, What would a clinician or pharmacist need to know about kidney function, medicines, and supplements?
For caregivers, specific descriptions are more useful than assigning a cause. “I noticed pauses followed by gasping” conveys an observation; “you need magnesium” assumes an explanation the research hasn't established.
Support can preserve autonomy. The older adult's preferences and account of their sleep remain central, alongside information a loved one can contribute.
Bringing It All Together
The observational research and safety review cited above support a measured conclusion about magnesium and sleep apnea. Researchers have found associations involving magnesium status, but they haven't established supplementation as a treatment for airway collapse.
The distinction between blood concentration, dietary intake, and supplement use is central to interpreting those findings. So is the difference between feeling more rested and measuring fewer breathing interruptions.
Better understanding doesn't require a promise of a quick fix.
For older adults, supplement suitability also depends on context, including kidney function and medication use. Healthy-aging conversations can include balanced eating, enjoyable movement, social connection, and sleep routines without presenting those activities as substitutes for apnea evaluation or established treatment.
The useful outcome is a clearer conversation: what someone notices, what the research measured, and which questions need individualized interpretation.
Rx360 brings together Health Insights, Smart Technology, and Connected Care to support independent living and connection with loved ones. Visit Rx360 to explore how clear wellness information and connected support can help keep sleep-related observations part of the conversation while preserving your everyday autonomy.
Lower-Risk Medication Plan Checklist
Below is a practical checklist and step plan you can implement into your daily life:
-
List all medications
Include prescriptions, over-the-counter drugs, supplements, sleep aids, creams, patches, eye drops, and inhalers.
-
Mark fall-risk drugs
Flag medicines that cause dizziness, sleepiness, confusion, blurred vision, low blood pressure, or low blood sugar.
-
Ask for a medication review
Bring the list to a pharmacist or prescriber.
-
Review after any warning sign
Request a new medication check after a fall, near-fall, new prescription, dose change, dizziness, or confusion.


